Elderly Care Explained: Comparing Solutions in Assisted Living, Independent Living, and Nursing Homes
Business Name: BeeHive Homes of Albuquerque West
Address: 6000 Whiteman Dr NW, Albuquerque, NM 87120
Phone: (505) 302-1919
BeeHive Homes of Albuquerque West
At BeeHive Homes of Albuquerque West, New Mexico, we provide exceptional assisted living in a warm, home-like environment. Residents enjoy private, spacious rooms with ADA-approved bathrooms, delicious home-cooked meals served three times daily, and the benefits of a small, close-knit community. Our compassionate staff offers personalized care and assistance with daily activities, always prioritizing dignity and well-being. With engaging activities that promote health and happiness, BeeHive Homes creates a place where residents truly feel at home. Schedule a tour today and experience the difference.
6000 Whiteman Dr NW, Albuquerque, NM 87120
Business Hours
Choosing the ideal setting for an older adult is among those choices that feels both immediate and frustrating. Families frequently call me after a fall, a hospitalization, or a sudden scare, and the first sentence is often the very same: "I do not even know where to begin."
The problem is that we utilize "senior care" as if it were one thing. It is not. Independent living, assisted living, nursing homes, and respite care all serve very various purposes. When you understand what each does well, and just as importantly what it does not do, the path forward ends up being clearer.
This guide walks through how these settings compare in daily reality, not simply on glossy pamphlets. The goal is to help you match a genuine individual, with real strengths and constraints, to the ideal level of support.
How the main senior care settings vary in practice
On paper, the differences look tidy. Independent living is for active elders. Assisted living adds assist with everyday jobs. Nursing homes offer 24/7 competent nursing. In reality, the lines blur, and every building has its own culture.
It helps to believe less about labels and more about 3 axes:
- How much hands on help with day-to-day activities is available.
- How much medical oversight and monitoring exists on site.
- How much control the person keeps over their schedule and lifestyle.
Each kind of elderly care balances those three factors differently.
Independent living: way of life first, support second
Independent living communities are frequently the first formal step in senior care, though lots of residents do not believe of them as "care" at all. They see them as a more secure, easier way to live without the concern of home maintenance.
These neighborhoods generally provide personal apartment or condos, communal dining, housekeeping, maintenance, arranged transportation, and a calendar of social and wellness activities. Staff are present, however they are not there to supply hands on personal care.
From the resident's perspective, independent living feels closest to routine house life. They lock their own door, select their own regimens, and choose which services to use. The safety net is lighter: pull cords, emergency situation pendants, and personnel who can respond to an event, but not always a nurse in the building 24/7.
Independent living can be a strong fit when:
- The person is still able to handle individual care, medications, and mobility with little or no help.
- Driving is ending up being difficult or hazardous and they need transportation solutions.
- Loneliness is sneaking in and social isolation is a concern.
- The home environment has become too much, such as stairs, backyard work, or consistent repairs.
What independent living does refrain from doing well is continuous medical management. If your parent has unstable heart failure, requires insulin adjustments, or deals with complex wound care, an independent setting will likely rely heavily on outdoors home health nurses and frequent center visits. Personnel might discover that "something is off," but they are not there to manage medical crises.
A common misunderstanding is that staff in independent living will immediately "watch" on residents' medication adherence, nutrition, and hydration. Some neighborhoods provide additional charge based health checks, however the standard expectation is independence. Issues can go unnoticed longer than families realize, especially if the resident is private or decreasing their struggles.
Assisted living: everyday assistance and a mid level of oversight
Assisted living sits between independent living and nursing homes. It is designed for people who can no longer manage safely on their own, yet do not need constant proficient nursing care.
Residents normally reside in private or semi personal apartments. The building design may look comparable to independent living, however the personnel mix and expectations vary. Assistants are available to aid with what professionals call activities of daily living: bathing, dressing, grooming, toileting, moving, and in some cases consuming. Medication administration is frequently a significant service, with staff arranging pill boxes, advising residents, and physically giving out medications.
Nursing existence in assisted living is variable. In some states, regulations need a nurse on site for a specific number of hours each day. In others, a nurse may be shared across several buildings or offered on call. That distinction matters for individuals with more than routine medical needs.
In practical terms, assisted living works well when someone:
- Needs regular assist with one or more individual care jobs, such as showering, dressing, or getting securely in and out of bed.
- Has medication programs that they can not dependably handle alone.
- Is at risk of falls and takes advantage of more regular check ins.
- Has moderate to moderate cognitive decrease but can still take part meaningfully in day-to-day decisions.
Compared to independent living, there is more structure in assisted living. Meals are normally served at set times, care tasks are scheduled, and staff documentation is more official since of regulatory expectations.
Families often assume assisted living can "do whatever" except a ventilator. That is not precise. Assisted living is not a mini medical facility. Normal constraints include:
- No capability for constant heart, oxygen, or telemetry monitoring.
- Limited capability to handle complicated behavioral concerns in advanced dementia.
- Restrictions around feeding tubes, complex IV medications, or frequent suctioning.
- Inconsistent capability to handle late phase Parkinson's or other conditions that need extensive, hands on care sometimes per hour.
When requires move beyond what assisted living can securely provide, nursing homes (likewise called proficient nursing facilities) get in the picture.
Nursing homes: healthcare and 24/7 supervision
Nursing homes provide the greatest level of care in the basic senior care continuum short of a medical facility. They are certified as health care facilities, staffed with nurses and assistants all the time, often with on site access to physical, occupational, and speech therapy.
Residents in nursing homes normally fall under 2 broad categories. First are short stay clients who come for rehabilitation after a medical facility stay, for example following a hip fracture or stroke. Second are long term homeowners whose persistent conditions or functional constraints are too substantial for assisted living.
In a nursing home, every resident has a customized care strategy reviewed frequently by an interdisciplinary team. Medication management is comprehensive. Important signs and weight are tracked. Laboratory draws, wound treatments, catheter care, and oxygen modifications become part of routine operations.
That level of oversight is important for individuals who:

- Need knowledgeable nursing services everyday or near daily.
- Cannot reliably transfer or rearrange themselves, raising threat for pressure injuries.
- Have advanced dementia with considerable behavioral concerns or wandering.
- Require complex medical devices such as feeding tubes or frequent IV medications.
The trade off is environment and autonomy. Nursing homes feel more medical. Shared spaces prevail, specifically under Medicaid financing. Daily regimens are formed around personnel workflows and medical requirements. Citizens still have rights and options, however that freedom exists inside a healthcare framework.
One practical point: families frequently ask whether moving a loved one to a nursing home implies "quiting." In my experience, it is much better framed as matching the intensity of support to the strength of requirement. For somebody who is risky without very close tracking, a nursing home can reduce emergency room visits, offer structure to days and nights, and ease household caregivers who have actually been operating at an unsustainable pace.
Respite care: short term relief and test drives
Respite care is the most misconstrued piece of elderly care. Rather of being a long term placement, respite is momentary care supplied to offer the typical caregiver a break or to bridge a transition.
Respite can occur in numerous settings:
- In home, where a paid caretaker or nurse comes for a set number of hours or days.
- In assisted living or nursing homes, where the person remains for a restricted duration, regularly 1 to 30 days.
- In adult day programs, where the individual goes to throughout daytime hours only.
Families often find respite care after a crisis, such as a caregiver's hospitalization or burnout. Used proactively, it can prevent those crises. I have actually seen spouses keep their loved one in the house for many years longer because they integrated in a routine rhythm of respite, such as one weekend a month or a week each quarter.
Respite remains in assisted living likewise serve another valuable function: they let everybody see how an individual adapts to communal living without a permanent dedication. You discover how they sleep, whether they join activities, and just how much staff assistance they truly require. That info shapes longer term decisions and can correct overoptimistic or overpessimistic assumptions.
One constraint of respite care is accessibility. Communities might have designated respite houses, or they may offer respite just when a regular apartment is briefly uninhabited. Planning ahead helps.
Comparing the settings side by side
Although I do not recommend basing decisions exclusively on checklists, it assists to see how these care types align on a few core dimensions.
|Element|Independent living|Assisted living|Nursing home|| ----------------------------|--------------------------------------------|---------------------------------------------------|---------------------------------------------------|| Primary focus|Lifestyle and convenience|Assistance with daily jobs and fundamental health requires|Detailed medical and personal care|| Medical personnel on site|Very little, frequently none on website|Aides plus restricted nursing hours|Nurses and assistants 24/7|| Individual care support|Not routinely provided|Yes, arranged and as needed|Yes, comprehensive and frequent|| Medication management|Resident managed, some suggestions possible|Personnel handled and documented|Fully handled with drug store oversight|| Typical resident profile|Independent, socially oriented|Requirements assist with ADLs, some cognitive problems|Considerable medical or cognitive needs|| Apartment or condo/ space type|Private apartments|Personal or semi private houses|Private or shared rooms, more scientific design|| Payment sources|Mainly private pay|Mostly private pay, some waivers in some states|Mix of Medicare (short stay), Medicaid, private|
This table simplifies a messy reality. Laws vary by state, and specific neighborhoods stretch or narrow their service lines within those constraints. When you tour, you are not just taking a look at the category. You are examining how that particular building translates its role.
Signs that independent living may no longer be enough
Many households postpone shifts since they fear disturbing their loved one, or they hope that "a bit more help" will be enough. That is understandable. Still, certain patterns typically indicate that independent living no longer matches the person's needs.
Examples consist of duplicated medication errors, such as missed dosages, double dosing, or confusion about brand-new prescriptions. Another red flag is increased participation from the community's personnel. If housekeeping, dining space teams, or front desk personnel are frequently calling you about concerns, they may currently be stretching beyond what their role allows.
Frequent falls, even if small, recommend that movement or judgment has altered. So do episodes of getting lost within the building, leaving ranges on, or blending day and night. When next-door neighbors start functioning as de facto caretakers, signing in numerous times a day, the arrangement is beginning to surpass what independent living can securely support.
The natural next step for a number of these homeowners is assisted living in the exact same school, if available, or in a similar community. Familiar surroundings ease the shift, especially for someone with cognitive impairment.
When assisted living reaches its limits
On the surface area, assisted living may look calm and capable. Locals are dressed, public spaces tidy, and personnel seem mindful. Beneath, staff might currently be pushing their certified scope of practice to keep particular homeowners stable.
Practical tipping points consist of:
- Recurrent hospitalizations for infections, cardiac arrest, or breathing issues in spite of good everyday care.
- Needs for 2 or more staff to securely transfer the person, specifically if those transfers occur many times a day.
- Aggressive or hazardous habits related to dementia that put other residents or staff at risk.
- Complex medical devices that requires experienced oversight, not simply basic training.
In those scenarios, even the very best assisted living team eventually needs to confess that a nursing home environment is safer. This is not failure. It shows the different legal and useful structures under which each kind of structure operates.
An easy procedure for choosing the right level of senior care
Families often request a formula. There is no perfect one, but there is a procedure that regularly clarifies thinking. Use the following as a working sequence, not a stiff rulebook.
- Start with function, not age. Note what the individual can do independently, what they can do with triggering, and what they can refrain from doing even with help. Be completely sincere about bathing, toileting, transfers, consuming, and handling medications and money.
- Identify the top three security concerns. Falls, roaming, avoiding meds, driving, cooking, or vulnerability to frauds are all typical. Rank them by threat and impact. This matters more than counting diagnoses.
- Map existing support. Who is currently helping and how often: partner, adult kid, next-door neighbor, paid aide, or nobody. Include travel range, work schedules, and caretaker health. Lots of strategies stop working because they presume more family availability than really exists.
- Factor in medical intricacy. Consider how typically the individual sees medical professionals, whether they require frequent monitoring, and how rapidly they decline when ill. A fairly stable 90 years of age may fit assisted living better than a medically fragile 70 year old.
- Weigh worths and preferences. Some older grownups would accept more threat to protect independence. Others focus on security and medical backup. Put those desires beside the realities above and ask where you can jeopardize and where you cannot.
When families stroll through this procedure on paper, the proper setting normally emerges. If function is high and safety issues are mainly about social seclusion, independent living may be adequate. If personal care requirements and medication complexity control, assisted living becomes appealing. When safety and medical complexity are both high, nursing home level care, perhaps preceded by a respite stay, is worthy of major consideration.
How expense and financing vary throughout settings
The monetary side of elderly care frequently surprises individuals more than the psychological side. A couple of guiding principles assist set realistic expectations.
Independent and assisted living are mainly private pay in the United States. Month-to-month charges typically range from a couple of thousand dollars to upper four figures or more, depending upon area, house size, and service levels. Some states offer Medicaid waiver programs that subsidize assisted living for qualified low earnings homeowners, but slots are restricted and waiting lists common.
Nursing homes blend three main payers: Medicare, Medicaid, and personal pay. Medicare covers short-term experienced stays after qualifying hospitalizations under particular rules. It does not pay forever for long term custodial care. When assisted living in albuquerque nm Medicare protection ends, homeowners either pay independently or, if eligible, shift to Medicaid. Medicaid becomes the main payer for a large share of long stay residents.
Respite care can be paid out of pocket, through specific insurance plans, or in minimal cases through veteran benefits or regional relief programs. Costs differ widely by setting, but everyday rates in neighborhoods frequently align with their basic everyday space and board plus care fees.
Before touring communities, it is smart to collect:

- Rough monthly spending plan from earnings and assets.
- Insurance information: Medicare Advantage vs standard Medicare, any long term care insurance, veteran status.
- A sense of how long existing resources should last, especially if one spouse is much healthier and will outlast the other.
That financial map will not determine every decision, yet it avoids heartbreaking surprises months into a placement.
Using respite care tactically, not simply in crisis
Families who thrive over the long term often use respite care before they feel desperate. A daughter who cares for her mother in the house might set up a week of respite in assisted living two times a year, timed to her own busiest work durations. A son might generate in home respite every Saturday afternoon so he can attend his kids' games or simply rest.
These planned breaks serve a number of functions. They secure the main caretaker's health, give the older adult direct exposure to various environments and individuals, and test how well existing support arrangements are working. If your loved one struggles significantly during a short respite stay, that is data. It may imply they need a various sort of setting quicker than anticipated, or that more steady shaping of expectations is required.
I have also seen respite end up being a bridge throughout significant life occasions, like a caregiver's surgical treatment or relocation. Instead of rushing into an ill fitting long term positioning, households utilize a 30 day respite stay while they sort out what comes next. That buffer decreases pressure and allows more thoughtful choices.
When brother or sisters and families disagree
Disagreements about elderly care are nearly unavoidable. One sibling might promote a nursing home, another insist that "Mom assured she would never ever go to a center." Beneath those positions often lies a mix of regret, worry, and different memories of childhood roles.
What helps is anchoring discussions in observable truths rather than analyses. Rather of "She is great at home," define the number of times somebody helps her shower weekly, the number of falls taken place in the last month, or how often the stove was left on. Concrete information softens absolutist positions.
Bringing in a neutral professional assessment can likewise break stalemates. Geriatric care managers, social employees connected to centers or hospitals, or palliative care groups can examine medical records, observe function, and suggest appropriate levels of care. When a non family professional states, "Based upon her existing needs, assisted living would be unsafe, she qualifies for nursing home care," it carries weight.
If possible, involve the older adult honestly. Sugarcoating often backfires. Numerous seniors value being dealt with as partners instead of as problems to be resolved in trick. The way you frame alternatives matters. Expressions like "We want to discover a place where you are safe and surrounded by individuals, and where we can visit as kids, not simply as caretakers" frequently land better than "You can not live alone any longer."
Final ideas: matching individual, requires, and setting
All of these care settings exist for a factor. Independent living supports way of life and neighborhood when upkeep and driving ended up being too heavy. Assisted living bridges self-reliance and hands on assistance, supporting life for those who require daily assistance however not continuous medical care. Nursing homes concentrate skilled resources around those who are most medically and functionally vulnerable. Respite care secures caretakers and gives everybody area to breathe.
The right choice is the one that reasonably deals with current risks, prepares for near term changes, respects the older grownup's values as much as possible, and fits within financial and household limits. Perfect services are rare. Good enough options, reviewed and changed over time, are not just possible but common.
Elderly care is not a one time choice. It is a progressing process. The more you understand what each setting truly offers, the much better equipped you are to make each action of that journey with clearness and compassion.
BeeHive Homes of Albuquerque West provides assisted living care
BeeHive Homes of Albuquerque West provides memory care services
BeeHive Homes of Albuquerque West provides respite care services
BeeHive Homes of Albuquerque West offers support from professional caregivers
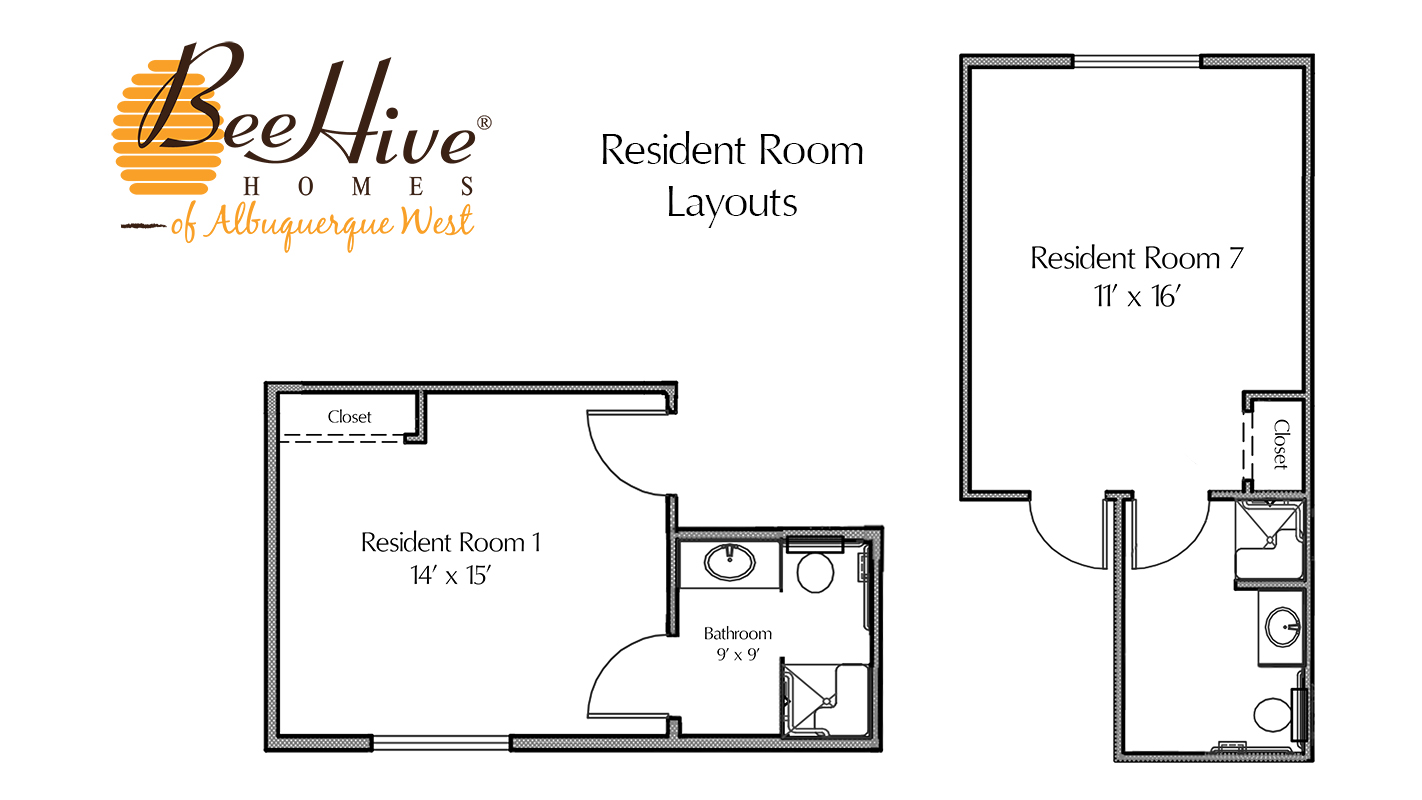
BeeHive Homes of Albuquerque West offers private bedrooms with private bathrooms
BeeHive Homes of Albuquerque West provides medication monitoring and documentation
BeeHive Homes of Albuquerque West serves dietitian-approved meals
BeeHive Homes of Albuquerque West provides housekeeping services
BeeHive Homes of Albuquerque West provides laundry services
BeeHive Homes of Albuquerque West offers community dining and social engagement activities
BeeHive Homes of Albuquerque West features life enrichment activities
BeeHive Homes of Albuquerque West supports personal care assistance during meals and daily routines
BeeHive Homes of Albuquerque West promotes frequent physical and mental exercise opportunities
BeeHive Homes of Albuquerque West provides a home-like residential environment
BeeHive Homes of Albuquerque West creates customized care plans as residents’ needs change
BeeHive Homes of Albuquerque West assesses individual resident care needs
BeeHive Homes of Albuquerque West accepts private pay and long-term care insurance
BeeHive Homes of Albuquerque West assists qualified veterans with Aid and Attendance benefits
BeeHive Homes of Albuquerque West encourages meaningful resident-to-staff relationships
BeeHive Homes of Albuquerque West delivers compassionate, attentive senior care focused on dignity and comfort
BeeHive Homes of Albuquerque West has a phone number of (505) 302-1919
BeeHive Homes of Albuquerque West has an address of 6000 Whiteman Dr NW, Albuquerque, NM 87120
BeeHive Homes of Albuquerque West has a website https://beehivehomes.com/locations/albuquerque-west/
BeeHive Homes of Albuquerque West has Google Maps listing https://maps.app.goo.gl/R1bEL8jYMtgheUH96
BeeHive Homes of Albuquerque West has Facebook page https://www.facebook.com/BeehiveABQW/
BeeHive Homes of Albuquerque West won Top Assisted Living Homes 2025
BeeHive Homes of Albuquerque West earned Best Customer Service Award 2024
BeeHive Homes of Albuquerque West placed 1st for Senior Living Communities 2025
People Also Ask about BeeHive Homes of Albuquerque West
What is BeeHive Homes of Albuquerque West monthly room rate?
Our base rate is $6,900 per month, but the rate each resident pays depends on the level of care that is needed. We do an initial evaluation for each potential resident to determine the level of care needed. The monthly rate is based on this evaluation. We also charge a one-time community fee of $2,000.
Can residents stay in BeeHive Homes of Albuquerque West until the end of their life?
Usually yes. There are exceptions, such as when there are safety issues with the resident, or they need 24 hour skilled nursing services.
Does Medicare or Medicaid pay for a stay at Bee Hive Homes?
Medicare pays for hospital and nursing home stays, but does not pay for assisted living as a covered benefit. Some assisted living facilities are Medicaid providers but we are not. We do accept private pay, long-term care insurance, and we can assist qualified Veterans with approval for the Aid and Attendance program.
Do we have a nurse on staff?
We do have a nurse on contract who is available as a resource to our staff but our residents' needs do not require a nurse on-site. We always have trained caregivers in the home and awake around the clock.
Do we allow pets at Bee Hive?
Yes, we allow small pets as long as the resident is able to care for them. State regulations require that we have evidence of current immunizations for any required shots.
Do we have a pharmacy that fills prescriptions?
We do have a relationship with an excellent pharmacy that is able to deliver to us and packages most medications in punch-cards, which improves storage and safety. We can work with any pharmacy you choose but do highly recommend our institutional pharmacy partner.
Do we offer medication administration?
Our caregivers are trained in assisting with medication administration. They assist the residents in getting the right medications at the right times, and we store all medications securely. In some situations we can assist a diabetic resident to self-administer insulin injections. We also have the services of a pharmacist for regular medication reviews to ensure our residents are getting the most appropriate medications for their needs.
Where is BeeHive Homes of Albuquerque West located?
BeeHive Homes of Albuquerque West is conveniently located at 6000 Whiteman Dr NW, Albuquerque, NM 87120. You can easily find directions on Google Maps or call at (505) 302-1919 Monday through Sunday 10am to 7pm
How can I contact BeeHive Homes of Albuquerque West?
You can contact BeeHive Homes of Albuquerque West by phone at: (505) 302-1919, visit their website at https://beehivehomes.com/locations/albuquerque-west, or connect on social media via Facebook
Take a short drive to Weck's which serves as a comfortable restaurant choice for seniors receiving assisted living or senior care during planned respite care outings.